
Miller Classification of Gingival Recession: Classes I, II, III, and IV
Machine translation
Original article is written in ES language (link to read it) .
What is Miller's classification of gingival recession?
The original classification of gingival recession, published more than three decades ago, described four classes of recession. For example, Miller Class III recession included several variations without complete root coverage. However, today, new surgical techniques have potentially enabled clinicians to achieve complete root coverage in cases of interdental bone loss. Currently, the interdental papilla plays an important role in dentistry. This article presents a new classification of interdental papilla morphology that emphasizes the importance of papilla width and height. In addition, an updated classification of periodontal terms will be presented.
More useful and up-to-date information about gingival recession is available in the webinar Localized Recession: Definition, Classification, Etiology, and Risk Factors .
The original article, published more than 30 years ago, described four classes of recession in the classification. A common feature of Miller Class I and Class II recession was the absence of interdental bone or soft-tissue loss. The difference between Class I and Class II recession was whether the recession extended beyond the mucogingival junction.
However, the original article did not emphasize the distinction between attached and unattached gingiva. Class III recession included two variants in which complete root coverage was not achieved. The first case described an extracted tooth without interdental bone or soft-tissue loss, whereas the second, in contrast, was associated with bone and soft-tissue loss. New surgical techniques enable clinicians to achieve complete root coverage in cases of interdental bone loss. Miller Class IV describes interdental recession with an absent papilla, meaning that the root cannot be covered.
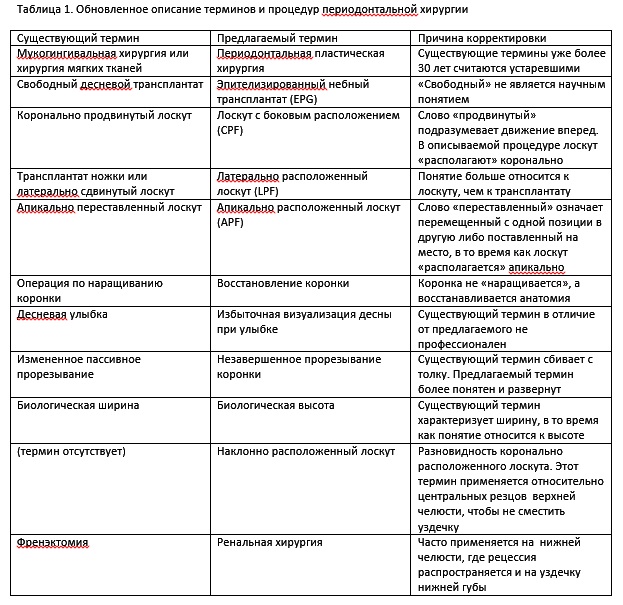
Since there is some confusion in periodontal terminology that requires review, a new classification of these terms will be presented (Table 1).
Periodontal plastic surgery
When the original classification of marginal gingival recession was published, periodontists emphasized the treatment of periodontal disease rather than esthetics. Surgery unrelated to disease was called mucogingival surgery. Since the introduction of the concept of periodontal plastic surgery, periodontics has entered a new stage of development.
Unlike mucogingival surgery, periodontal plastic surgery sought not only to achieve the best possible functional result, but also to achieve an esthetic outcome. At the same time, treatment options for marginal recession were limited to laterally positioned flaps (LPF) and coronally positioned flaps (CPF), and, on the palatal side, epithelialized graft placement (EPG).
Despite the positive esthetic results of using LPF and CPF, EPG had serious disadvantages that not only led to repeat surgery, but also to gingival discoloration with subsequent proliferation of connective tissue, resulting in scar formation.
A major breakthrough in the treatment of recession came with the introduction of subepithelial connective tissue grafting (SCTG). In this method, the graft was covered with SCTG, which provided bilaminar circulation, an additional blood supply, and improved graft survival. The graft was harvested from the palatal side, reducing discomfort. Allograft and xenograft materials were replaced with native tissue, avoiding damage to the palate.
Thus, in light of the development of surgical methods for treating recession, Miller's original classification was expanded and a new classification of the gingival papilla was added.
Miller classification: Classes I, II, III, and IV
Class I and II recession
Class I and II recessions are characterized by preservation of bone or soft tissue, suggesting complete root coverage is possible. The difference between the two classes is the presence or absence of attached gingiva (Figure 1).
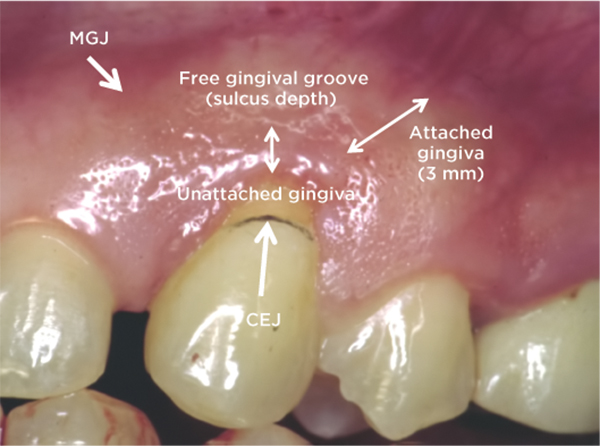
Fig.1 Class I recession. Note that the free gingival groove separates the unattached gingiva from the attached gingiva.
Class I recession was initially described as recession that did not extend to the mucogingival junction (MGJ). If gingiva remained on the buccal surface, this was classified as Class I recession. In fact, if the gingiva is unattached, there is a “hidden recession,” which should be classified as Class II recession (Fig. 2).
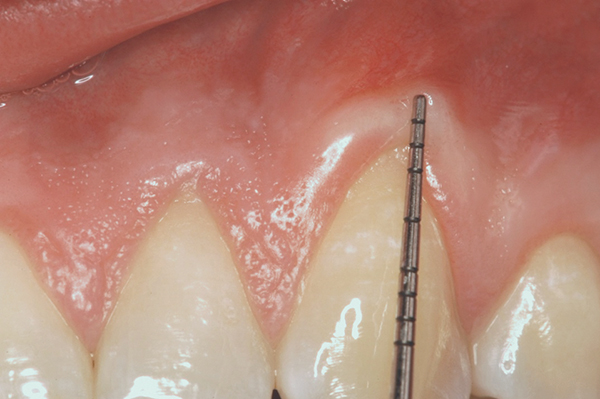
Fig.2 Class II recession. Although gingiva may remain on the buccal surface, if it is unattached, this is Class II recession. The only way to determine this accurately is to check whether the probe extends beyond the mucogingival junction.
Therefore, wherever gingiva is present on the buccal surface, it must be carefully examined to determine whether it is attached.
Although complete root coverage is achieved in both Class I and Class II recessions, treatment modalities may vary. For example, if normal keratinized epithelial tissue is present in Class I recession, the simplest root coverage procedure, CPF, may be suggested. In Class II recession, a soft-tissue flap will be needed. Treatment of Class II recession requires more complex tissue grafting procedures. Combining Classes I and II into a single classification category can lead to confusion when choosing treatment. In the author's opinion, the new recession classification presented at the 2017 World Workshop on the Classification of Periodontal Diseases did not take this into account.
Class III recession
Class III recession was initially described as interdental bone and/or soft-tissue loss or tooth extraction. In this clinical situation, only partial root coverage can be achieved. This can be achieved using tunnel technology, but further root coverage cannot be achieved in every case of Class III recession (Fig. 3 and Fig. 4). At the time of the original classification, the focus of periodontal treatment was on maintaining gingival health and function rather than gingival esthetics. In most cases, the underlying issue was more esthetic than functional, and even an attempt at partial root coverage was not considered.
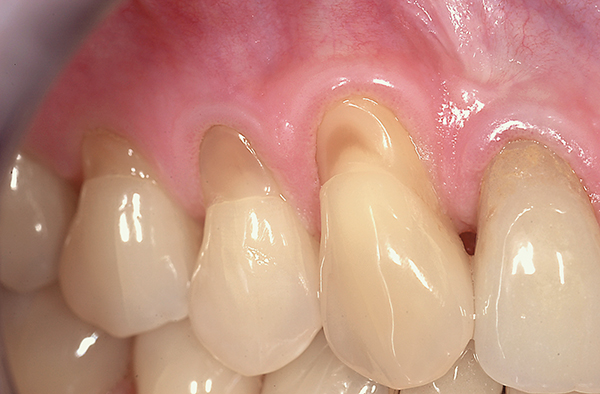
Fig. 3 Class III recession (Fig. 3) was originally described as bone and/or soft-tissue loss or tooth extraction. Only partial root coverage can be achieved. Using a tunnel technique, dissecting and elevating the papilla can provide additional root coverage in some Class III recessions (Figure 4).
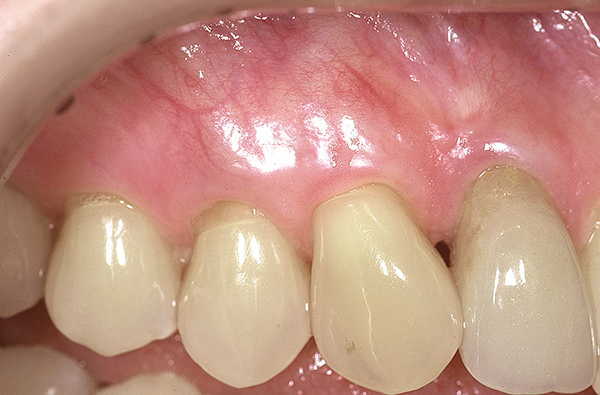
Fig. 4
Class IV recession
In Class IV recession, regardless of its severity, root coverage cannot be achieved because there is no interdental papilla (Fig. 5).
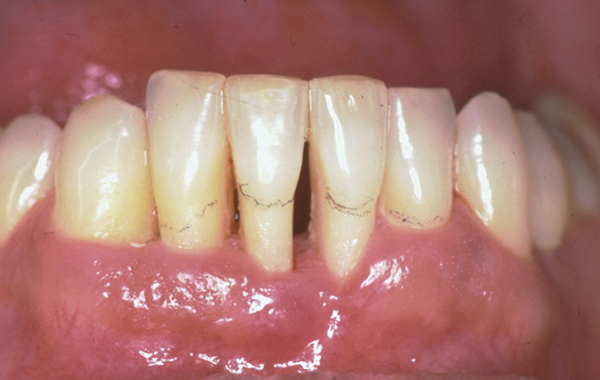
Fig. 5 In Class IV recession, regardless of the severity of the recession, complete root coverage cannot be achieved because there is no papilla.
Importance of interdental papillae in root coverage
In 1992, Tarnow et al. demonstrated that the height of a normal interdental papilla is 5 mm. In 1998, Nordland and Tarnow published a classification of interdental papillary recession. However, it did not take into account the width or buccolingual size of the papilla. With the advent of the tunnel technique, interdental papillae attain normal volume, especially in the mesiodistal direction. A papilla of sufficient size on the buccal surface provides a good blood supply to the graft. This helps improve root coverage in proximal areas according to Miller Class III.
Classification of interdental papillae: Types A, B, and C
According to the author's observations, papillae can be divided into three types: A, B, and C (Table 2).
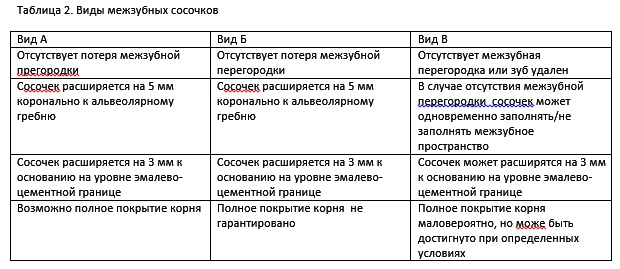
Types A and B are similar in that the interdental bone is preserved. The papilla extends 5 mm coronally from the alveolar crest.
They differ in width. A Type A papilla is ≥3 mm wide at the base (Fig. 6), and a Type B papilla is <3 mm wide (Fig. 7). A Type C papilla is characterized by the absence of interdental bone or tooth loss. (Figure 8). That is, in all cases where interdental bone is absent, the papilla is classified as Type C.
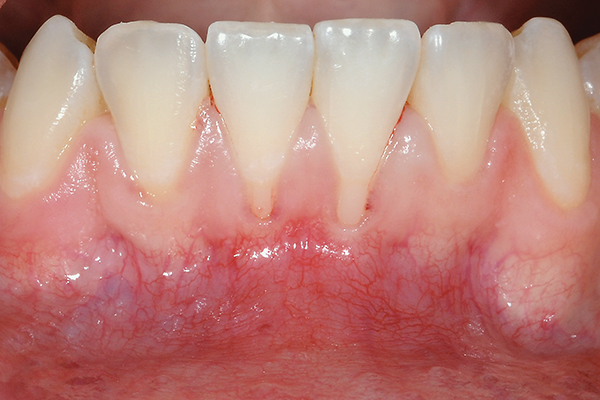
Fig. 6 Class II recession with Type A papillae. Papillae ≥3 mm.
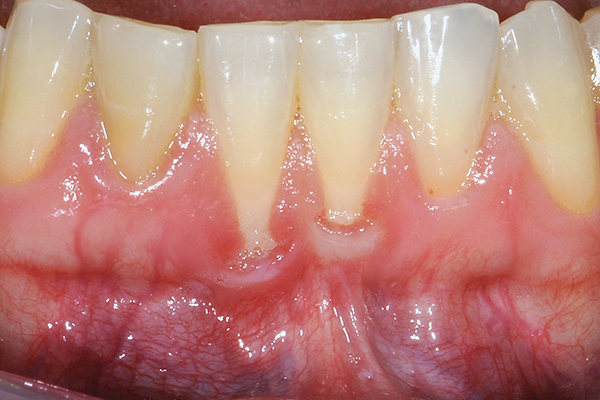
Fig. 7 Class II recession with a Type B papilla between the central incisors. Papilla <3 mm.
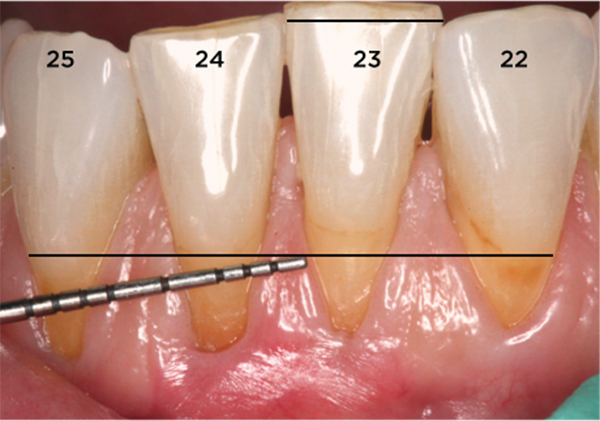
Fig. 8 The papilla between teeth 2.4 and 2.5 is Type A. The papilla between teeth 2.2 and 2.3 is Type C. Note the distal interdental recession on tooth 2.3 and the mesial recession on tooth 2.2.
When bone loss is present, the papilla may extend ≥5 mm toward the crown. Sometimes it is difficult to accurately identify and classify a papilla as Type C because the shape of the papilla does not always correspond to the shape of the bone. Since there is bone loss in the interdental space, but the papilla remains unchanged, hidden recession is observed. A distinguishing feature is loss of the interdental septum. The width of a Type C papilla may be ≤3 mm.
Class I and Class II recessions have Type A or Type B papillae. Class III recession has a Type C papilla, and Class IV recession has no papilla. Type A papillae provide a favorable environment for graft survival, whereas Type B papillae provide a more limited source of blood supply and stability as their width decreases, reducing the predictability of complete root coverage.
In the anterior maxilla, the width of a Type A papilla is ≥3 mm. In contrast, interdental papillae in the mandible are rarely wide, especially when the teeth are crowded. The width, height, and distance from the crest affect the amount of root coverage that can be achieved in Class III recession. Clinical experience shows that adequate papillary width is necessary for an adequate blood supply and suture placement in soft tissue.
Conclusion
With the advent of tunnel technology and subsequent modifications, complete root coverage has become possible in Class III recessions. Papilla morphology becomes an important factor in these areas. In addition to the characteristics of the Type C papilla described above, the papilla must have sufficient volume in the labiolingual direction to survive coronal advancement. Under ideal conditions, an increase in papillary height of up to 2 mm can be achieved. The advantages of the tunnel technique include complete graft coverage, delamination and elevation of the interdental papillae, and avoidance of external vertical or horizontal incisions.
Learn more about this topic in the online course Advanced Treatment of Periodontal Diseases .
https://www.aegisdentalnetwork.com/